
Biocompatibility Testing for Medical Devices
Biocompatibility testing for medical devices helps show that a device and its materials are biologically safe for the body they contact. I3CGLOBAL helps manufacturers plan ISO 10993 evaluation, arrange testing through accredited laboratories and prepare evidence for EU MDR and US FDA.
The basics
What Is Biocompatibility Testing for Medical Devices?
Biocompatibility testing assesses whether a device or its materials could cause an unacceptable biological response, such as cell damage, irritation, an allergic reaction or systemic toxicity. It is part of a wider biological evaluation under the ISO 10993 series.
The final device is what matters. Individual materials may look safe, but manufacturing residues, additives, sterilisation and material combinations can all change the result. Testing is therefore only one source of evidence, alongside chemistry, existing data and risk assessment.

Which Regulations Require Biological Safety Evidence?
Biocompatibility testing is a means to an end. The real requirement is to show biological safety, within a risk management process.
| Source | Requirement | What It Means |
|---|---|---|
| EU MDR Annex I, Section 10 | Chemical, physical and biological properties, including compatibility of materials with tissues, cells and body fluids. | Provide evidence for the final device and its intended contact. |
| EU MDR Annex II, Section 6.1 | Pre-clinical data in the technical documentation, including biocompatibility. | Tests or justifications go into the MDR technical file. |
| EN ISO 10993-1:2025 | Requirements and principles for evaluating biological safety within a risk management process. | Reported as harmonised under the MDR in June 2026. |
| US FDA guidance | FDA guidance on using ISO 10993-1 in premarket submissions. | Check the guidance and FDA recognised editions for your 510(k). |
| ISO 14971 | Risk management for medical devices. | Biological risks belong in the risk management file. |
What Changed in ISO 10993-1:2025?
The sixth edition, published in November 2025, moves further from a checklist of tests towards a biological evaluation integrated with ISO 14971. Existing plans based on older editions should be reviewed against it.
| Topic | Change | Practical Effect |
|---|---|---|
| Approach | Evaluation sits within risk management. | Build the evaluation from hazards and exposure, not from a test menu. |
| Endpoint tables | One matrix is replaced by four tables based on contact type. | Re-check your endpoint selection. |
| Device categories | The externally communicating category is removed and split by type of contact. | Older device categorisation may need updating. |
| Contact duration | Exposure is based on contact days. | Repeated short daily use may count as longer exposure. |
| Foreseeable misuse | Reasonably foreseeable misuse must be considered. | Add it from the planning stage. |
| Expertise | Evaluators need appropriate expertise. | Keep evidence of competence. |
| Animal testing | New methods are emphasised, and animal tests need a justification. | Use chemistry and existing data first. |
When Is Biocompatibility Testing Needed?
Biological evaluation applies to devices with direct or indirect contact with the body. Whether new testing is needed depends on the existing evidence. In practice, you should consider these factors:
- The nature of contact, such as skin, mucosa, blood, tissue, bone or an implant
- The frequency and duration of contact, including repeated use
- All body-contacting materials, including indirect fluid paths
- Additives, processing aids, residues and sterilisation residues
- Geometry and surface properties, including wear particles
- The patient population, such as neonates or pregnant patients
- Changes in material, supplier, process, packaging or sterilisation
A device with a long history may still need new work if it has changed, or if the earlier evidence does not meet the current standard. Conversely, a well-justified evaluation may reduce or avoid some tests.
What Are the Common Biocompatibility Tests?
The evaluation decides which endpoints must be addressed. These are the most commonly considered, with the relevant part of the ISO 10993 series.
| Endpoint | What It Assesses | ISO 10993 Part |
|---|---|---|
| Cytotoxicity | Cell damage or death | Part 5 |
| Sensitisation | Allergic reaction | Part 10 |
| Irritation | Local skin or tissue reaction | Part 23 |
| Acute and repeated systemic toxicity | Effects on the whole body | Part 11 |
| Genotoxicity, carcinogenicity and reproductive toxicity | Effects on DNA, cancer risk, fertility and development | Part 3 |
| Implantation | Local tissue effects after implantation | Part 6 |
| Hemocompatibility | Effects on blood | Part 4 |
| Chemical characterisation | Materials and extractables or leachables | Part 18 |
| Toxicological risk assessment | Whether chemical exposure is acceptable | Part 17 |
| Sample preparation | Extraction and reference materials | Part 12 |
| Ethylene oxide residues | Residues from EO sterilisation | Part 7 |
Not every device needs every test. Record why each endpoint is addressed by testing, by existing data or by another justification.
What Are the 7 Steps in the Biocompatibility Process?
A clear process prevents unnecessary animal testing and repeated work.
- Describe the deviceRecord materials, processing, contact, duration, users and foreseeable misuse.
- Collect existing dataReview supplier information, earlier tests, literature and clinical experience.
- Write the evaluation planPrepare a biological evaluation plan linked to your risk management plan.
- Characterise the chemistryIdentify materials and evaluate extractables or leachables where needed.
- Select and run testsChoose a laboratory, agree protocols and test representative final devices.
- Assess the resultsReview findings and carry out toxicological risk assessment where needed.
- Report and maintainPrepare the biological evaluation report and review it after changes and post-market findings.
Chemistry
Why Does Chemical Characterisation Matter?
Chemical characterisation can identify what may leach from a device and how much a patient could be exposed to. A toxicologist can then assess the risk under ISO 10993-17.
It may reduce some biological testing, but it is not an automatic replacement. It also helps when materials change, because it gives a basis for comparing the old and new device. Keep analytical limits, extraction conditions and the rationale in your file.

What Is the Difference Between In Vitro and In Vivo Testing?
In vitro tests take place outside a living organism, such as a cytotoxicity test using cultured cells. In vivo tests take place in a living organism. The standards ask that animal testing is considered only when it is justified, and that alternatives are used where they are validated.
| Point | In Vitro | In Vivo |
|---|---|---|
| Setting | Cells or tissue models in a laboratory. | A whole living organism. |
| Typical use | Cytotoxicity and some genotoxicity testing. | Certain systemic toxicity and implantation studies. |
| Timing | Often earlier in the evaluation. | After chemistry, in vitro work and data review. |
| Duration | Often shorter. | Weeks to more than several months. |
| Key control | Validated method and suitable extraction. | Scientific justification and animal welfare under Part 2. |
Why Do Devices Fail Biocompatibility Testing?
A failed test does not always mean the device must be redesigned, but the cause must be investigated. These issues are common causes of failures or review questions:
- Residues from moulding, cleaning or adhesives
- Colourants or additives that were not disclosed by suppliers
- Testing raw material rather than the final device
- Extraction conditions that do not suit the device
- Sterilisation or ageing effects not considered
- Contact duration understated for repeated use
- No toxicological risk assessment for chemistry findings
- A plan based on an older edition of ISO 10993-1, with no gap assessment
- Reports that do not trace back to the production device
How Do Contact and Duration Affect Biocompatibility Testing?
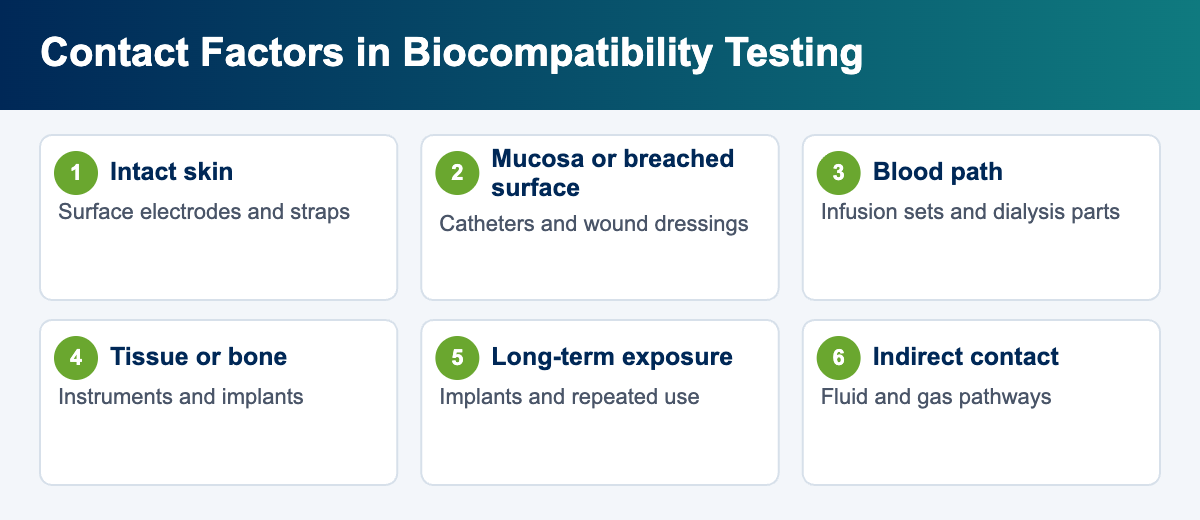
The type and length of contact are the main drivers of the evaluation. ISO 10993-1:2025 uses separate tables for different types of contact, so use the current tables when you select endpoints.
| Contact Factor | Examples | What to Consider |
|---|---|---|
| Intact skin | Surface electrodes and straps | Skin reactions, wear time and repeated use. |
| Mucosal or breached surfaces | Urinary catheters and wound dressings | Greater exposure and local tissue effects. |
| Blood path | Infusion sets and dialysis parts | Hemocompatibility and systemic effects. |
| Tissue or bone | Surgical instruments and implants | Implantation, degradation and local effects. |
| Long-term exposure | Implants and repeated-use devices | Chronic toxicity, genotoxicity and carcinogenicity, as applicable. |
| Indirect contact | Fluid paths and gas pathways | Substances that may reach the patient through the device. |
Duration is commonly grouped as limited (up to 24 hours), prolonged (more than 24 hours to 30 days) and long-term (more than 30 days). Repeated use can move a device into a higher category, so count the contact days carefully.
Examples
What Biocompatibility Testing Might Different Devices Need?
These simple examples show how the evaluation may differ. They are not a test plan, since your materials and data may change the outcome.
- Skin electrode, short use: cytotoxicity, sensitisation and irritation are often considered.
- Wound dressing: also consider systemic effects, depending on the wound and duration.
- Blood contacting tubing: hemocompatibility is added to the local and systemic endpoints.
- Long-term implant: implantation, chronic toxicity, genotoxicity and carcinogenicity are often considered.
- Dental or orthopaedic device: consider wear particles, degradation and tissue contact.
How Should You Prepare Samples for Testing?
Many failed or rejected studies come from poor sample selection, not from an unsafe device. Part 12 of ISO 10993 covers sample preparation and reference materials. Check these points before you ship samples:
| Point | What to Confirm |
|---|---|
| Representative samples | Samples are final finished devices, or a justified equivalent, from a controlled process. |
| Worst-case selection | Size, colour or variant selection is justified. |
| Sterilisation | Samples have gone through the intended sterilisation, including any maximum cycles. |
| Ageing | The effect of ageing is considered, where relevant. |
| Extraction | Solvent, ratio, time and temperature suit the device and the test. |
| Traceability | Batch, lot and manufacturing records are linked to the report. |
Agree the protocol before testing. It is far easier to change an extraction ratio or test article at this stage than to explain the choice later to a reviewer.
What Should You Do if a Biocompatibility Test Fails?
Do not simply repeat the test until it passes. Reviewers expect an investigation and a rationale.
- Confirm the resultCheck controls, sample handling, extraction and any laboratory deviations.
- Look for the causeReview materials, residues, processing, cleaning and sterilisation.
- Use chemistryIdentify substances that could explain the response.
- Assess the riskConsider the clinical relevance with a qualified toxicologist or evaluator.
- Correct the device if neededChange the material or process, then assess the effect on other evidence.
- Document the decisionRecord the investigation in the risk file and evaluation report.
A cytotoxicity response, for example, can be a useful signal, but it does not always decide the matter by itself. Interpretation should consider the device, the exposure and the other data.
How Do EU and FDA Biocompatibility Expectations Differ?
Both markets use ISO 10993, but they do not always read it the same way. Plan for both markets at the start if you intend to sell in each.
| Topic | EU MDR | US FDA |
|---|---|---|
| Main framework | MDR Annex I, with EN ISO 10993 standards. | FDA guidance on the use of ISO 10993-1. |
| Reviewer | Notified Body, for most devices above Class I. | FDA reviewer during premarket submission. |
| Edition | Check harmonised status and transition. | Check the FDA recognised standards database. |
| Documents | Evaluation in technical documentation. | Rationale and test summaries in the submission. |
| Materials | CMR and endocrine-disrupting substances are addressed in Annex I, Section 10.4. | Chemical and toxicological expectations are set out in FDA guidance. |
How Do You Choose a Biocompatibility Laboratory?
Laboratory selection affects whether a reviewer accepts your data. Ask for evidence on each of these points:
- ISO/IEC 17025 accreditation covering the specific ISO 10993 methods
- Good Laboratory Practice status for relevant in vivo studies
- Experience with your device type and sample format
- Chemistry capability, with suitable analytical methods
- Access to qualified toxicologists
- Clear, signed reports with protocol details and any deviations
Our wider medical device testing guide explains how biological work fits with electrical, mechanical and sterility evidence.
How Does I3CGLOBAL Help?
We help manufacturers demonstrate biological safety and provide medical devices biocompatibility testing through accredited laboratories for manufacturers worldwide. Use our fee calculator for an early estimate.
Evaluation plan
Prepare a plan based on device contact, materials and existing data.
Testing coordination
Arrange tests, samples and protocols with accredited laboratories.
Gap assessment
Review older reports against ISO 10993-1:2025 and current requirements.
Chemistry and toxicology
Coordinate chemical characterisation and risk assessment.
Evaluation report
Prepare the final report for your technical file.
Templates
Work with I3CGLOBAL
Plan Your Biocompatibility Testing for Medical Devices
Tell us about your device, materials and contact type, and our team will suggest the next step.
- Biological evaluation planning
- Testing through accredited laboratories
- ISO 10993-1:2025 gap review
- Reports for CE marking and FDA 510(k) submissions
Request your proposal
Share your device details and materials, and we will prepare a proposal.
FAQs
Biocompatibility Testing: Frequently Asked Questions
What is biocompatibility testing?
Biocompatibility testing assesses whether a device or material could cause an unacceptable biological response in the body. It is part of a biological evaluation under the ISO 10993 series and is linked to risk management.
Is biocompatibility testing mandatory?
Biological safety evidence is required where a device contacts the body. Specific tests are not always mandatory, because a justified evaluation may rely on chemistry, existing data or earlier test results.
What are the most common biocompatibility tests?
Cytotoxicity, sensitisation and irritation are the most commonly considered. Other endpoints can include systemic toxicity, genotoxicity, implantation and hemocompatibility, depending on the type and duration of contact.
What is the latest version of ISO 10993-1?
ISO 10993-1:2025 is the latest edition, published in November 2025. EN ISO 10993-1:2025 is reported as harmonised under the EU MDR in June 2026. Confirm how your Notified Body expects you to transition.
Do I need to retest if my report uses ISO 10993-1:2018?
Not automatically. Perform a gap assessment against the current edition. Existing data may remain valid if you can justify it, but some endpoints or contact assumptions may need new work.
Can raw material certificates replace device testing?
Usually they cannot replace evaluation of the final device. Processing, additives, residues and sterilisation can change biological safety. Supplier data can support the evaluation, though.
How long does biocompatibility testing take?
It depends on the tests. Some in vitro tests take weeks, while chronic or carcinogenicity studies can take many months. Plan for samples, protocols and laboratory availability.
Is animal testing required?
Not always. Animal testing should be justified, and validated alternatives, chemistry and existing data should be considered first. Some endpoints may still need in vivo evidence.
What is the difference between biocompatibility testing and a biological evaluation report?
Testing produces data on specific endpoints. The biological evaluation report brings together all data, including testing, chemistry and literature, and concludes on biological safety.
Does the FDA accept ISO 10993 testing?
FDA uses ISO 10993-1 through its own guidance, and adds specific expectations. Check the current FDA guidance and recognised standards database before you finalise your test plan.